

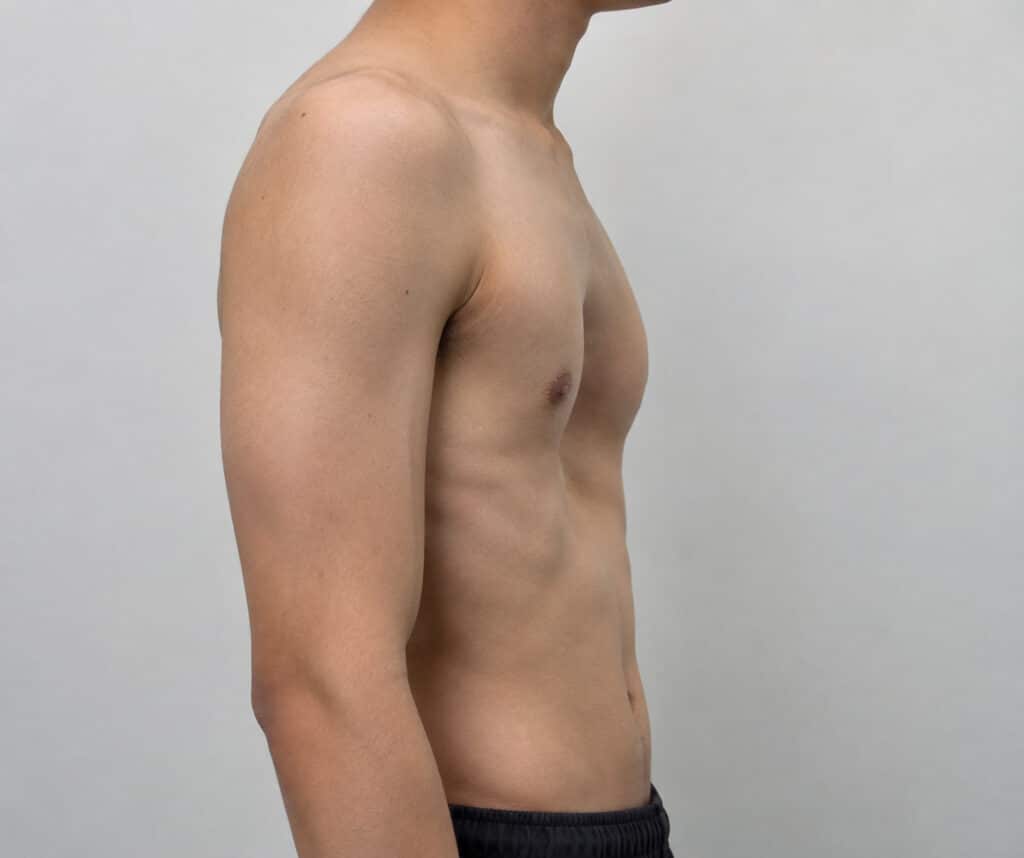
Funnel chest surgery may be considered when a sunken breastbone causes significant physical symptoms, affects heart or lung function, or creates a severe chest wall deformity. For patients and parents considering pectus excavatum surgery, the decision to operate is rarely based on appearance alone.
The severity of the deformity, symptoms, imaging results, heart and lung function, age and individual circumstances all contribute to treatment planning. Understanding when surgery may be recommended, how the main procedures work and what recovery involves can make discussions with a thoracic specialist clearer and more productive.
Funnel chest (pectus excavatum) is a sunken chest wall deformity that can compress the heart and lungs, cause breathlessness and chest pain, and significantly affect self-confidence.
Surgery is usually considered when there is clear evidence of severity, often including a Haller Index of 3.25 or higher, alongside physical symptoms or evidence of cardiac or respiratory compression.
The Nuss procedure is a commonly used minimally invasive operation for pectus excavatum, with bar removal typically planned 2 to 3 years later.
NHS-funded pectus surgery is generally reserved for patients meeting strict clinical criteria, while private assessment may offer faster access and greater flexibility in treatment planning.
Surgery is only one option. Some patients benefit from breathing exercises, physiotherapy and vacuum bell therapy, depending on their age and the severity of the deformity.
What Is Funnel Chest (Pectus Excavatum)?
Funnel chest and pectus excavatum describe the same condition: a sunken breastbone caused by abnormal growth of the ribs and cartilage in the chest wall. The sternum is pulled inward, creating a central or asymmetrical depression across the front of the chest.
Pectus excavatum is the most common congenital chest wall deformity. It affects about 1 in 400 births in the UK and is roughly three to five times more frequent in boys than girls. The condition often becomes more noticeable during the growth spurt between ages 11 and 14, when rapid skeletal development can deepen the depression.
Common associated features include poor posture, sloping shoulders and abnormally shaped ribs. Some families appear to have a genetic tendency towards chest wall deformities, and relatives may occasionally develop pectus carinatum, where the breastbone projects outward rather than inward.
In mild cases, funnel chest may primarily affect the appearance of the chest. In severe pectus excavatum, however, the depression can compress the heart and lungs and affect exercise capacity. The psychological effects should also be recognised. Research reports that 80% of patients feel bothered by their chest appearance and 65% report feelings of anxiety, while some experience depression or significant loss of confidence.
Have a question about your diagnosis?
A consultation gives you a personalised plan — not a generic estimate.
How Is Pectus Excavatum Diagnosed?
Diagnosis usually begins with a clinical examination. A GP or healthcare professional assesses the chest wall shape, symmetry and depth of the depression. If pectus excavatum appears significant or is associated with symptoms, referral to a thoracic or chest wall specialist may follow.
Important questions include whether the patient experiences breathlessness on exertion, chest pain, palpitations, fatigue, reduced exercise tolerance or concerns about the appearance of the chest. These symptoms help determine whether the deformity is primarily cosmetic or may also be affecting physical function.
Several investigations can then help assess severity and its effect on the heart and lungs.
Test | Purpose |
CT scan or low-dose CT | Calculates the Haller Index and Correction Index and shows possible organ compression |
MRI | Provides a radiation-free assessment and may be particularly useful in younger patients |
Chest X-ray | Provides an initial assessment of chest wall shape |
Pulmonary function tests | Measure lung function and airflow |
Echocardiogram / ECG | Assess heart function, compression and rhythm |
Cardiopulmonary exercise test (CPET) | Provides an objective measurement of exercise capacity |
The Haller Index and Correction Index are commonly used measurements of chest wall severity. Additional investigations, including cardiac MRI, may be appropriate when compression or displacement of the heart is suspected.
"After multiple failed consultations elsewhere, Mr Scarci identified exactly what was wrong and operated within two weeks. Recovery was smooth and I'm back to normal life."
When Is Funnel Chest Surgery Recommended?
Funnel chest surgery is generally considered when the deformity is moderate to severe and is associated with significant symptoms, measurable functional impairment or evidence that the chest wall is affecting the heart or lungs.
Objective severity is often assessed using a Haller Index of 3.25 or higher or a Correction Index of around 28% or more on CT or MRI. These measurements are not considered in isolation. Symptoms, exercise capacity, imaging findings and cardiac or respiratory effects also influence whether an operation is appropriate.
Typical indications may include:
Breathlessness with modest exertion
Reduced exercise capacity compared with peers
Chest pain or pressure
Palpitations or documented arrhythmias
Fatigue or exercise intolerance
Documented compression or displacement of the heart or lungs
Severe pectus excavatum can cause breathing difficulties and reduced exercise tolerance that become more noticeable during adolescence or early adulthood. Surgery is often performed during the teenage years or early adulthood while the chest wall remains relatively flexible, although adults can also undergo successful correction.
Current NHS England policy supports pectus surgery for patients with very severe physiological symptoms who meet the required clinical criteria. Surgery is not routinely funded purely for cosmetic concerns, so evidence of functional impact is particularly important within the NHS pathway.
Patients with mild, asymptomatic pectus excavatum are generally managed without immediate surgery. Observation, posture work, breathing exercises, physiotherapy and reassurance may be more appropriate when heart and lung function remain unaffected.
Not sure about your treatment options?
Mr Scarci provides expert consultations typically within one week of contact.
Assessing Severity: Chest Wall Shape, Heart and Lung Function
The decision to recommend surgery is based on a combination of chest wall anatomy, objective measurements and the effect of the deformity on cardiopulmonary function.
Haller Index
The Haller Index is the most widely used measurement. It is calculated from chest imaging by comparing the internal width of the chest with its front-to-back depth at the deepest point of the deformity.
A Haller Index below 3 is generally associated with a milder deformity, while an index of 3.25 or above is commonly used as a threshold indicating severe pectus excavatum.
Correction Index
The Correction Index provides an additional measurement and can be especially useful for asymmetric pectus excavatum, where the Haller Index may not fully describe the deformity.
It represents the percentage of chest wall depression requiring correction. A value of approximately 28% or more is often considered significant when evaluating surgical suitability.
Heart and Lung Function
Pulmonary function tests and cardiopulmonary exercise testing help assess whether the deformity affects breathing and exercise capacity. European consensus guidance indicates that a VO₂ max below 85% predicted may support evidence of functional impairment. Some patients have relatively normal spirometry at rest despite experiencing significant breathlessness during exercise.
Cardiac assessment usually involves echocardiography and may include cardiac MRI to identify displacement or compression of the heart.
Mr Marco Scarci, a consultant thoracic surgeon in London specialising in chest wall deformities and minimally invasive thoracic surgery, also considers posture, spinal alignment (such as scoliosis), symptoms, and overall chest wall anatomy when assessing whether pectus excavatum requires treatment.
"I was diagnosed in March with a rare condition. My local hospital said it was inoperable due to the size of the mass. Mr Scarci reassured me the thymoma was resectable. I was booked for surgery the following week where he successfully removed the entire tumour."
Surgical Options for Funnel Chest: Nuss and Ravitch Procedures
There are two main surgical approaches used to correct pectus excavatum: the minimally invasive Nuss procedure and open techniques such as the modified Ravitch procedure.
The Nuss Procedure
The Nuss procedure, also known as minimally invasive repair of pectus excavatum or MIRPE, is performed through small incisions on either side of the chest. One or more curved metal bars are passed behind the sternum and rotated, pushing the breastbone forward into a corrected position.
The Nuss procedure for pectus avoids the larger anterior incision associated with traditional open surgery. The bar generally remains in place for 2 to 3 years while the chest wall remodels, after which it is removed during a shorter procedure.
The Ravitch Procedure
The Ravitch procedure is an open surgical approach involving a longer incision across the front of the chest. The surgeon removes or reshapes abnormal rib cartilage and repositions the sternum. A temporary support bar, strut or plate may sometimes be used.
It can be particularly useful for patients with rigid, markedly asymmetric or complex deformities, or in selected cases where previous surgery or anatomy makes a minimally invasive approach less suitable.
Feature | Nuss Procedure | Ravitch Procedure |
Approach | Minimally invasive / keyhole | Open surgery |
Incisions | Two small side incisions | Longer front-of-chest incision |
Often suited to | Flexible chest walls and suitable symmetric defects | Rigid, asymmetric or complex deformities |
Implant | Curved metal bar or bars | Strut or plate in some cases |
Implant duration | Usually 2 to 3 years | Variable |
The choice of operation depends on age, anatomy, deformity pattern, previous surgery and the experience and recommendation of the surgical team.
Want a specialist opinion on your condition?
Get a clear answer from a surgeon who will be with you throughout.
The Nuss Procedure: What Happens Before, During and After Surgery
Before Surgery
Preparation begins with specialist assessment. The surgeon reviews chest imaging, heart and lung investigations and symptoms before determining whether the Nuss procedure is appropriate.
Pre-operative preparation typically includes blood tests, an anaesthetic assessment and advice about smoking cessation, general fitness and breathing exercises. Patients should also understand the risks of thoracic surgery before giving informed consent.
On the Day
Under general anaesthesia, small incisions are made on either side of the chest wall. A thoracoscope, or keyhole camera, is inserted so the surgeon can visualise the inside of the chest while positioning the curved metal bar behind the sternum.
Once correctly positioned, the bar is rotated to push the breastbone forward. It is then secured to reduce the risk of movement.
Recovery in Hospital
Recovery begins with pain management, breathing exercises and early mobilisation. Some patients spend the first night in a monitored or high-dependency setting.
Modern pain-management strategies may include patient-controlled analgesia, regional anaesthetic techniques and, in some specialist centres, cryoablation of intercostal nerves. Early breathing exercises are encouraged to maintain lung expansion and reduce respiratory complications.
Hospital stays vary, but many patients remain admitted for around 3 to 7 days, with some fit younger patients discharged within approximately 3 to 5 days.
Recovery at Home
Initial recovery at home usually takes around 4 to 6 weeks. Heavy lifting, contact sport and excessive twisting are generally restricted during the early healing period.
During the first 6 to 12 weeks, activity is gradually increased according to pain and surgical advice. Some patients can return to desk-based work or study at around six weeks, while lighter exercise may begin after approximately 6 to 8 weeks, when recovery is progressing appropriately.
Recovery after chest wall deformity treatment also depends on the type of correction performed, chest wall flexibility and the patient’s overall health. Physiotherapy, posture work and breathing exercises can support the chest wall as it adapts to its corrected shape.
Nuss bar removal is usually planned 2 to 3 years later and is generally a shorter procedure with a quicker recovery than the original operation.
Non-Surgical and Supportive Treatments
Not everyone with pectus excavatum needs surgery. Younger patients with mild deformities, good cardiopulmonary function and limited symptoms may benefit from conservative treatment.
Vacuum Bell Therapy
A vacuum bell is a suction device placed over the chest to gradually lift the sternum. It is usually worn regularly over many months or years and tends to be most effective in younger patients whose chest walls remain flexible.
The treatment may improve pectus excavatum in selected patients, although results vary and long-term correction is less predictable than surgical treatment for severe deformities.
Physiotherapy and Exercise
Pectus excavatum treatment may include physiotherapy focused on posture, strengthening the back and core muscles, and specific breathing exercises designed to improve chest expansion.
Exercise does not structurally correct a severe chest wall depression, but it can improve posture, fitness, breathing mechanics and the overall appearance of the chest.
Psychological Support
Pectus excavatum can significantly affect self-confidence and body image, particularly during adolescence. Anxiety, low mood and avoidance of activities such as swimming or changing in communal areas should not be dismissed simply because they are psychological rather than physical symptoms.
Counselling or psychological support may therefore form an important part of treatment, whether or not surgery is ultimately chosen.
Non-surgical treatment does not usually reverse severe pectus excavatum, but it may improve symptoms and quality of life and can be appropriate when surgery is not required or is being deferred.
Have a question about your diagnosis?
A consultation gives you a personalised plan — not a generic estimate.
NHS vs Private Funnel Chest Surgery in the UK
Access criteria and timelines differ between NHS-funded and private pectus excavatum treatment.
NHS Pathway
NHS England’s current commissioning position allows pectus surgery for patients with pectus excavatum causing very severe physiological symptoms, provided they meet the required criteria. The policy was most recently updated in August 2026.
Assessment typically considers objective severity, functional impairment and evidence involving the heart or lungs. A Haller Index of 3.25 or higher may form part of the assessment, but eligibility is not based on this number alone.
Purely cosmetic concerns are not sufficient for NHS-funded surgery. The NHS commissioning policy sets out the current eligibility requirements.
The ongoing RESTORE clinical trial, which began recruiting in 2024, is comparing surgical and non-surgical management in patients with severe pectus excavatum and may contribute further evidence about long-term cardiopulmonary outcomes.
Private Pathway
Private treatment can provide faster access to specialist consultation, diagnostic testing and surgery. Assessment may also allow broader consideration of symptoms, functional limitations, body image and overall quality of life when deciding whether surgery is appropriate.
Patients considering self-funded treatment can review pectus surgery costs before proceeding. Private surgery may also be covered by medical insurance depending on the policy and clinical indication.
Existing NHS scans, test results and referral letters can usually be reviewed during a private thoracic consultation, potentially reducing unnecessary duplication of investigations.
Risks, Benefits and Long-Term Outcomes of Funnel Chest Surgery
Pectus excavatum correction is major chest wall surgery, so the expected benefits need to be weighed carefully against the potential risks for each patient. Successful surgery can move the breastbone into a more natural position, create additional space for the heart and lungs, and improve exercise tolerance, chest discomfort and chest wall symmetry.
For some patients, the psychological benefits are also significant. Improved confidence, body image and willingness to participate in activities such as swimming or sport can contribute to a meaningful improvement in quality of life.
Recognised risks of funnel chest surgery include:
Significant post-operative chest wall pain
Temporary difficulty taking deep breaths
Wound infection
A small pneumothorax
Displacement of the Nuss bar
Less commonly, major bleeding, implant movement, metal sensitivity or the need for another operation
Modern pain-control techniques, careful patient selection and appropriate post-operative monitoring help reduce the impact of many of these complications. Serious complications are uncommon, with mortality reported at below 1%, although individual risk depends on age, anatomy, surgical technique and underlying health.
Long-term outcomes are generally favourable. Most patients maintain a stable correction following bar removal and can eventually return to normal exercise and sport. A small amount of residual asymmetry or natural settling may remain, but major recurrence is uncommon when surgery and bar removal are appropriately timed. Patients should discuss their individual risk profile, expected results and long-term goals with their surgeon before deciding to proceed.
Not sure about your treatment options?
Mr Scarci provides expert consultations typically within one week of contact.
Preparing for Consultation and Surgery With Mr Marco Scarci

Good preparation makes the consultation more useful and ensures any proposed treatment is based on a complete picture of the patient’s symptoms, anatomy, and previous investigations.
Before the appointment, write down symptoms such as breathlessness, chest pain, palpitations, fatigue, or reduced exercise tolerance, and note how they affect sport, work, school, or everyday activities. Bring any previous CT or MRI scans, lung function results, echocardiograms and referral letters where available.
During the consultation, Mr Scarci can examine the chest wall, review existing imaging and discuss whether the deformity is better suited to observation, conservative treatment or surgery. Complex cases may also involve a multidisciplinary thoracic team when additional imaging, respiratory assessment or specialist input is required. Both in-person and virtual consultations are available, which may be particularly useful for international patients or people travelling from elsewhere in the UK.
If surgery is recommended, preparation may include improving general fitness, stopping smoking or vaping, practising breathing exercises and arranging sufficient time away from work, university or school. Following principles that support healing after surgery can also help patients prepare for the early recovery period and reduce avoidable setbacks.
Home support is important during the first few weeks after discharge, when movement may still be restricted, and everyday tasks can be more difficult.
The decision to operate should remain collaborative. The aim is to determine whether surgery offers enough functional, structural and quality-of-life benefit to justify the procedure and recovery for the individual patient.
Frequently Asked Questions About Funnel Chest Surgery
At what age is funnel chest surgery usually performed?
Surgery is typically performed on patients aged 10 to 14 years, though many centres prefer the mid-teens to early adulthood, roughly 14 to 25, when most growth has occurred, and the chest wall remains flexible. Clinicians assess most children and young people individually. Younger children with very severe symptoms may occasionally be considered, and adults in their 30s or 40s can still benefit, although recovery time may be longer and open techniques such as the Ravitch procedure may be more appropriate.
Can breathing exercises or the gym correct pectus excavatum without surgery?
Exercise and breathing work cannot cure the structural chest wall deformity, but they can improve posture, build chest and back muscles, and make the deformity less noticeable. Targeted physiotherapy can also support lung function and exercise tolerance, which may be particularly helpful in mild to moderate pectus excavatum and during recovery after surgery. For severe funnel chest with significant heart and lung compression, surgery remains the most reliable way to structurally correct the deformity.
How painful is the Nuss procedure and how is pain managed?
The minimally invasive Nuss procedure is associated with significant chest wall discomfort during the first few days because the metal bar holds the sternum forward under tension. Modern pain-management strategies, including patient-controlled analgesia, regional blocks and cryoablation of intercostal nerves in some centres, can reduce the need for strong opioids and support earlier mobilisation. Severe pain commonly improves substantially over 2 to 4 weeks, although milder aching can continue for several months.
Will funnel chest surgery leave big scars?
The Nuss procedure typically leaves two relatively small scars on the sides of the chest wall, along with a small camera incision. These generally fade with time and may be partly hidden beneath the arms. The modified Ravitch procedure requires a longer incision across the front of the chest, which is more visible. Discuss scar position and any previous tendency to develop keloid or hypertrophic scars before surgery.
Can funnel chest come back after the bar is removed?
In most patients, correction remains stable once the cartilage has remodelled and the bar is removed after 2 to 3 years. A small degree of settling or residual asymmetry can occur, but major recurrence is uncommon, particularly when the timing of surgery and bar removal is appropriate. Long-term follow-up can help monitor chest wall shape and identify the few patients who may need further treatment.
